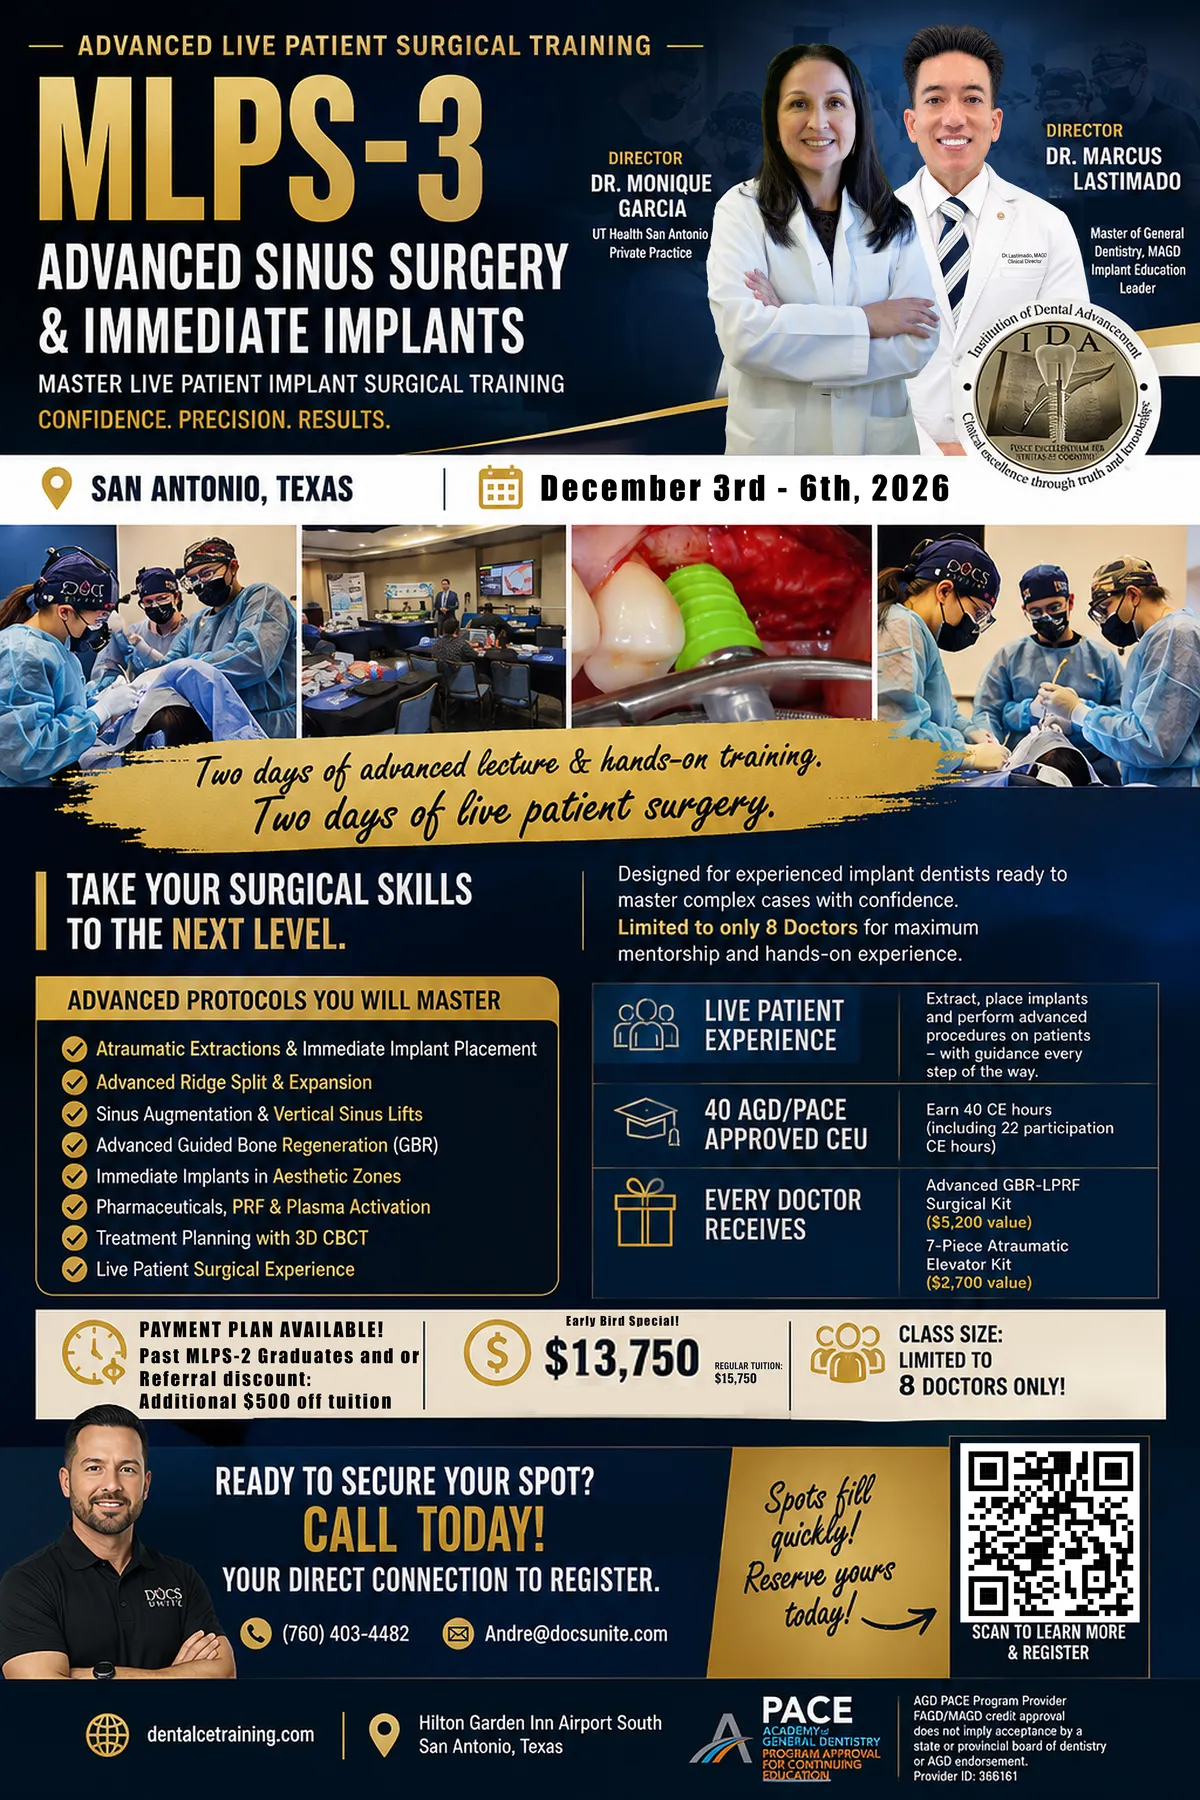
Course Program
*
Event
*
First Name
*
Last Name
*
Title / Position
*
Phone
*
Email
*
Practice or Business Name
*
Surgical Glove Size (Required for MLPS Courses)
AGD Number
Dental License State & Number
*
Implant Experience Level
*
Are you doing Implants now?
*
What are you most interested in learning?
*
Primary Area of Interest
Focus Area
Questions or Comments (Optional)
Email Communication Opt-In
Yes, I would like to receive emails from IDA
No
SMS/Text Message Opt-In
Yes, I would like to receive text message from IDA
No
I have read and agree to the event terms, CE certificate process, release of liability, photography/video/testimonial consent, and educational-use restrictions.
*
Yes, I agree
Submit Registration
Privacy Policy
|
Terms of Service