Hair Implant Evaluation Form
Email (To match with your file)
*
Date of Birth - Hair Evaluation
Smoke nicotine or take controlled substances? Yes (list them) - Hair Implant Evaluation
What date have the procedure done? - Hair Implant Evaluation
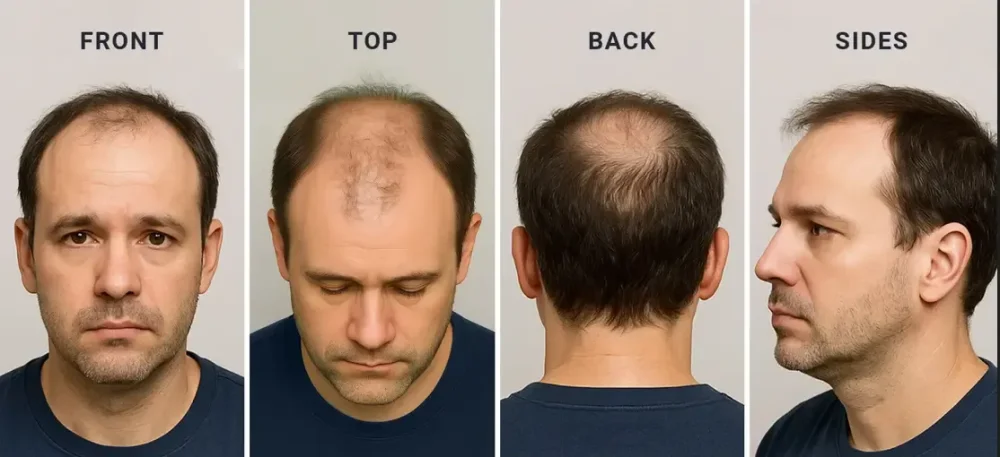
Top-down view - Hair Implant Evaluation
Back of head - Hair Implant Evaluation
Side profile - Hair Implant Evaluation
Front view - Hair Implant Evaluation
How long has the hair loss been progressing?
Hair loss worsening?
Yes
No
Areas to improve? (Check all)
Hairline
Crown
Temples
Top
Sides
Back
Overall density
Affected areas? (Check all)
Hairline
Crown
Temples
Top
Sides
Back
Goals? - Hair Implant Evaluation
Natural look
Maximum density
At what age did you first notice hair loss?
Medical conditions? Yes (list them) - Hair Implant Evaluation
Previous procedures? Yes (list them) - Hair Implant Evaluation
Drug allergies? Yes (list them) - Hair Implant Evaluation
Medications? Yes (list them) - Hair Implant Evaluation
Hospitalized in last 5 years? Yes (list them) - Hair Implant Evaluation
Fat burners/diet pills? Yes (list them) - Hair Implant Evaluation
Submit
First Touch Referrer
First Touch UTM Source
First Touch UTM Medium
First Touch UTM Campaign
First Touch GCLID
First Touch FBCLID
First Touch SP Src
First Touch Landing URL